 ultimate-guide
Newest Treatment for Treatment-Resistant Depression
Table of Contents
- What Counts as Treatment-Resistant Depression in 2026
- Treatment-Resistant Depression Treatment Options: A Head-to-Head Comparison
- Esketamine for Treatment-Resistant Depression: The Newest FDA-Approved Option
- SAINT Treatment for Depression: An Accelerated TMS Protocol
- Transcranial Magnetic Stimulation for Depression: Standard and Accelerated TMS
- ECT, VNS, and Experimental Options: What Is Approved and What Is Still Emerging
- After a Failed Antidepressant Trial: Building a Practical Treatment Pathway
- Maintenance, Relapse Prevention, and Safety Monitoring
- Frequently Asked Questions
Last Updated: October 13, 2026
What Counts as Treatment-Resistant Depression in 2026
Treatment-resistant depression is major depressive disorder that has not improved enough after at least two different antidepressant trials of adequate dose and duration. That definition matters because it separates ordinary treatment adjustment from a genuinely different clinical situation. At Trust and Care Mental Health Inc, we evaluate patients who have already tried two or more medications without adequate relief, and the first question is always whether those trials were truly adequate. Dose, duration, and adherence decide that.
Treatment-Resistant Depression Treatment Options: A Head-to-Head Comparison
The newest FDA-approved treatment for treatment-resistant depression is esketamine nasal spray. Several options carry FDA approval, and each trades speed against commitment, monitoring, and evidence. The table below summarizes how they compare; the sections that follow explain each in detail.
| Option | Typical Speed | FDA Status | Commitment |
|---|---|---|---|
| Esketamine nasal spray | Within days to weeks | Approved for TRD | Clinic visits, observation |
| SAINT accelerated TMS | Days | Approved protocol variant | Full-day sessions |
| Standard TMS | Several weeks | Approved | Daily visits, weeks |
| ECT | Days to weeks | Approved | Anesthesia, recovery time |
| VNS | Months | Approved for chronic TRD | Surgical implant |
How the Main Options Compare on Speed, Evidence, and Commitment
Speed is the clearest dividing line. Ketamine-based therapy and accelerated TMS can work faster than some other options, and ECT remains a highly effective option for severe cases. Evidence quality is strongest for ECT and standard TMS, which have decades of data behind them. Commitment runs the other way: faster options demand more intensive monitoring, while VNS requires surgery and months before benefit appears.
Esketamine for Treatment-Resistant Depression: The Newest FDA-Approved Option
Esketamine nasal spray is the newest FDA-approved treatment specifically indicated for treatment-resistant depression in adults. It is a derivative of ketamine that acts primarily on NMDA receptors rather than the serotonin, norepinephrine, and dopamine pathways standard antidepressants target.
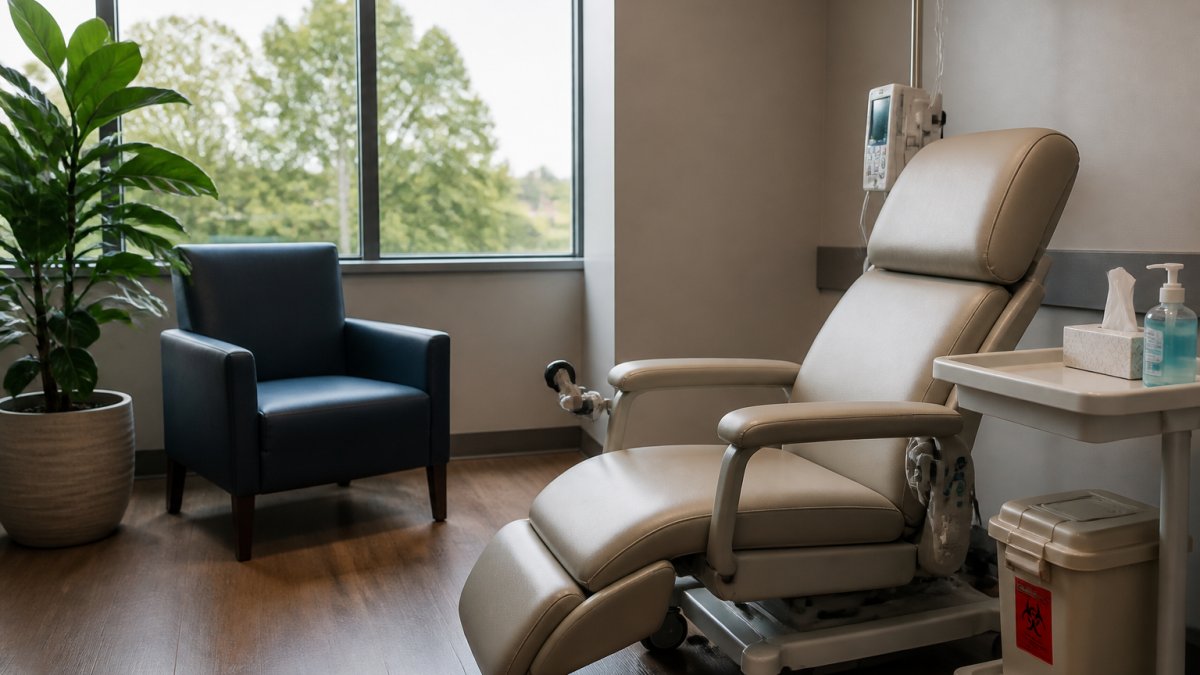
The FDA approved esketamine in 2019 for adults with major depressive disorder that has not responded adequately to at least two different antidepressant trials.
How Esketamine Is Given and What the Schedule Looks Like
Esketamine is administered in a certified clinical setting, not at home. The typical induction schedule is twice a week for the first four weeks, then once a week for weeks five through eight, with the frequency tapering further during maintenance based on response. Each session involves the nasal spray followed by a required observation period, usually about two hours, with blood pressure checked before and after. Patients cannot drive themselves home from a session.
Who It Is For, Who Should Avoid It, and What Monitoring Requires
Esketamine is intended for adults whose depression has not responded to at least two antidepressants of adequate dose and duration. It is not a first-line treatment, and it is not a substitute for an oral antidepressant, the approved regimen pairs the spray with an ongoing oral antidepressant.
Because esketamine can raise blood pressure and cause dissociation, sedation, and impaired judgment, the FDA requires administration under supervision in a certified setting with monitoring.
How Fast It Works and How Long Benefits Last
A common pattern reported in clinical use is improvement within days to a few weeks, though individual response varies widely and some patients do not respond at all. Benefit is not permanent: relapse after stopping is common, so maintenance sessions are typically continued on a schedule tailored to the person. Durability is one of the least predictable parts of esketamine care, which is why ongoing psychiatric follow-up matters as much as the initial course.
Cost, Coverage, and Access
Esketamine is a branded product, and cost and insurance coverage vary by plan. Many commercial plans and Medicare cover it for the approved indication, but prior authorization is common, and the required observation time means each session consumes a substantial part of a clinic day. Patients should expect to confirm coverage, copays, and the nearest certified treatment site before starting.
SAINT Treatment for Depression: An Accelerated TMS Protocol
SAINT treatment for depression is an accelerated form of transcranial magnetic stimulation that compresses weeks of daily sessions into a handful of days. Standard TMS delivers one session per weekday for several weeks. SAINT uses multiple sessions per day, targeting the same brain region with functional imaging to guide placement. The trade-off is intensity: patients commit to full treatment days rather than short daily visits. It remains a TMS protocol, so it carries TMS's general safety profile rather than a new one.
Transcranial Magnetic Stimulation for Depression: Standard and Accelerated TMS
Transcranial magnetic stimulation for depression uses magnetic pulses to stimulate underactive regions of the brain without anesthesia or medication. It is non-invasive, and patients stay awake throughout. Standard repetitive TMS is the most studied form, with a well-established safety record and no systemic side effects. Accelerated protocols like SAINT deliver the same underlying treatment on a compressed timeline. The main practical drawback of TMS generally is time: standard protocols require frequent visits for weeks, and results build gradually rather than overnight.
ECT, VNS, and Experimental Options: What Is Approved and What Is Still Emerging
The word "newest" hides an important distinction: some options are FDA-approved and available now, some are used off-label, and some are still investigational. This section separates them, with information current as of October 2026.
Electroconvulsive Therapy (ECT)
ECT is a highly effective approved treatment for severe depression, including cases with psychotic features, catatonia, or acute suicidal ideation, and it often works faster than medication. It is given under general anesthesia with a muscle relaxant, typically as a series of sessions two to three times per week for several weeks, followed by maintenance treatment in many cases. Modern ECT uses brief pulses and unilateral or bilateral electrode placement to reduce cognitive side effects, but short-term memory disruption remains the most common concern.
Vagus Nerve Stimulation (VNS)
VNS is FDA-approved for chronic or recurrent treatment-resistant depression in adults who have not responded to at least four adequate antidepressant trials. It requires surgical implantation of a device and a lead that stimulates the vagus nerve, and benefit typically takes months rather than days or weeks. Because it is implanted, it is generally considered after other options, and it carries surgical risks plus the possibility of voice changes, coughing, or throat discomfort during stimulation.
Transcranial Magnetic Stimulation (TMS) and Accelerated Protocols
TMS is FDA-approved for depression and is non-invasive, requiring no anesthesia. Standard repetitive TMS is delivered daily for several weeks, while accelerated protocols such as SAINT compress the same underlying treatment into a handful of full treatment days. TMS is generally well tolerated; the most common side effect is scalp discomfort, and the main serious risk is seizure, which is rare. Eligibility depends on factors such as implanted metal devices in or near the head and a history of seizures.
What Is Still Investigational
Deep brain stimulation for depression remains investigational in the United States and is generally available only through research protocols. Psychedelic-assisted therapies, including psilocybin and MDMA-assisted approaches, are not approved for routine depression care and remain under study, with regulatory decisions still evolving. Off-label ketamine infusions are used in some clinics but are not FDA-approved for depression, which means dosing, monitoring, and coverage are less standardized than for esketamine.
How to Compare These Options
| Option | FDA Status | Typical Onset | Administration | Key Considerations |
|---|---|---|---|---|
| ECT | Approved | Days to weeks | Anesthesia, series of sessions | Most effective for severe cases; memory side effects |
| VNS | Approved for chronic TRD | Months | Surgical implant | Requires four prior failed trials; ongoing programming |
| TMS / SAINT | Approved | Weeks (standard); days (accelerated) | Daily or full-day sessions | Non-invasive; seizure risk is rare |
| Esketamine | Approved for TRD | Days to weeks | Supervised nasal spray | Monitoring required; maintenance needed |
| Ketamine infusion | Off-label | Hours to days | IV infusion | Not FDA-approved for depression; variable oversight |
| DBS / psychedelics | Investigational | Varies | Trial protocols | Not routine care; long-term safety unknown |
Durability, Relapse, and Maintenance
Response rates for any single treatment are partial, and relapse after improvement is common. ECT often requires maintenance sessions; VNS is designed for long-term use; TMS may be repeated; esketamine is continued on a tapering schedule. The practical takeaway is that none of these treatments is a one-time fix, and ongoing psychiatric care is part of the plan rather than an afterthought.
After a Failed Antidepressant Trial: Building a Practical Treatment Pathway
A failed antidepressant trial is a data point, not a dead end. The practical sequence most psychiatrists follow looks like this:
- Confirm the trial was adequate in dose, duration, and adherence.
- Consider switching to a different antidepressant class or augmenting the current one.
- Add psychotherapy, particularly cognitive behavioral therapy, which pairs well with medication.
- Reassess symptom severity and any suicidal ideation.
- Move to a neuromodulation or ketamine-based option if medications keep failing.
- Match the next step to the person: speed, monitoring needs, and time commitment all count.
Medication switching and combination therapy remain reasonable first moves. When they fail, the newer options above become the conversation. A psychiatrist should guide each step, because eligibility and contraindications differ from person to person.
Maintenance, Relapse Prevention, and Safety Monitoring
Getting better is the first goal; staying better is the second. Response rates for any single treatment are partial, and relapse after improvement is common, which is why maintenance treatment matters. For esketamine, that means continuing scheduled sessions under monitoring.
Treatment-resistant depression is exhausting, and the search for something that finally works can feel endless. Trust and Care Mental Health Inc offers specialized care for treatment-resistant depression, including administration of FDA-approved Spravato esketamine nasal spray in a monitored clinical setting, with personalized medication management for adults, children, and older adults.
Frequently Asked Questions
What is the newest treatment for treatment-resistant depression?
The newest FDA-approved option is esketamine nasal spray, approved in 2019 for adults with treatment-resistant depression. It is used together with an oral antidepressant and must be given in a certified clinic under observation. Other newer approaches include accelerated TMS protocols, sometimes called SAINT, which compress a full course of magnetic stimulation into days rather than weeks. Ketamine infusions are used off-label for depression and are not FDA-approved for that purpose. Which option fits you depends on your history, health, and what your psychiatrist recommends.
How do I know if I have treatment-resistant depression?
Treatment-resistant depression is usually identified when symptoms do not improve enough after at least two different antidepressant trials at adequate doses and duration. Your psychiatrist reviews your medication history, symptom severity, and response to each trial. Inadequate response does not mean you cannot get better; it means the next step should match your specific pattern of symptoms. A full evaluation also checks for factors that can mimic resistance, such as bipolar disorder, thyroid problems, or untreated sleep apnea.
What is SAINT treatment for depression, and how is it different from standard TMS?
SAINT is an accelerated form of transcranial magnetic stimulation that delivers multiple sessions per day over about five days, rather than the standard course of daily sessions over four to six weeks. It targets a specific brain region using MRI-guided neuronavigation and has shown rapid improvement in some studies. Standard TMS is more widely available and covered by many insurance plans. Accelerated protocols may not be covered the same way, so it is worth checking benefits before starting.
Is esketamine covered by insurance, and how much does it cost?
Coverage varies by plan. Many commercial insurers and Medicare plans cover esketamine when criteria are met, such as a documented history of failed antidepressant trials. Because esketamine must be given under observation in a certified setting, the visit itself is part of the cost. Pricing depends on your insurance, the number of sessions, and the clinic. Ask your provider for a benefits check before starting, and request a written estimate so there are no surprises.


