 blog
5 Best Advanced Treatments for Major Depressive Disorder
Last Updated: October 23, 2026
Quick Summary
The 5 best advanced treatments for major depressive disorder are esketamine (Spravato), TMS, ECT, adjunctive medications, and advanced psychotherapy. Each is considered when standard care fails, and a board-certified psychiatrist matches the choice to your severity, treatment history, and schedule.
- Treatment-resistant depression means no response to two or more adequate antidepressant trials.
- Esketamine is given in a certified setting with at least two hours of monitoring per visit.
- TMS requires daily clinic sessions over several weeks with no anesthesia or recovery time.
- ECT moves up the list when depression is severe, psychotic, or life-threatening.
- Bring a written timeline of every antidepressant tried, with dose and duration, to your consultation.
Table of Contents
- When Standard Depression Care Is Not Enough
- Quick Comparison: 5 Advanced Treatments at a Glance
- 1. Esketamine Treatment for Depression (Spravato)
- 2. Transcranial Magnetic Stimulation for Depression
- 3. Electroconvulsive Therapy for Depression
- 4. Treatment-Resistant Depression Options: Adjunctive Medications
- 5. Psychotherapy as an Advanced Treatment for Major Depressive Disorder
- How to Choose the Right Advanced Depression Treatment
- Frequently Asked Questions
When Standard Depression Care Is Not Enough
Major depressive disorder is a serious condition, and for many people the first line of care, which usually means an antidepressant plus talk therapy, does not deliver full relief. This guide from Trust and Care Mental Health Inc walks through the 5 best advanced treatments for major depressive disorder, ranked by clinical grounding, eligibility, and practical fit.
Here is the honest starting point most guides skip: failing a medication does not mean you are untreatable. It means the treatment was not matched to your situation.
Signs You May Need Advanced Depression Treatment
Advanced treatment is generally considered when symptoms persist after adequate trials of standard therapy. A common approach is to review your medication history with a clinician and ask these questions:
- Have you completed at least two antidepressant trials at adequate dose and duration with little response?
- Do symptoms keep returning despite ongoing treatment?
- Are side effects making it hard to stay on your current regimen?
- Has depression limited work, sleep, appetite, or relationships for months?
Treatment-resistant depression is the clinical term for depression that has not responded to two or more adequate antidepressant trials. If that sounds like you, the five options below are the conversation to have with a psychiatrist.
Quick Comparison: 5 Advanced Treatments at a Glance
The table below summarizes eligibility, pace of relief, and the main trade-off for each treatment. Use it to frame your discussion with a clinician, not to self-select.
| Treatment | Best For | Typical Pace of Relief | Main Limitation |
|---|---|---|---|
| Esketamine (Spravato) | Treatment-resistant depression | Rapid, within days to weeks | Requires monitored dosing visits |
| TMS | Patients who prefer non-drug options | Weeks of daily sessions | Daily schedule commitment |
| ECT | Severe or life-threatening depression | Fast, often within weeks | Memory side effects |
| Adjunctive medications | Partial responders to antidepressants | Weeks to months | Side effect management |
| Advanced psychotherapy | Chronic or recurrent depression | Gradual, builds over months | Requires consistent attendance |
1. Esketamine Treatment for Depression (Spravato)
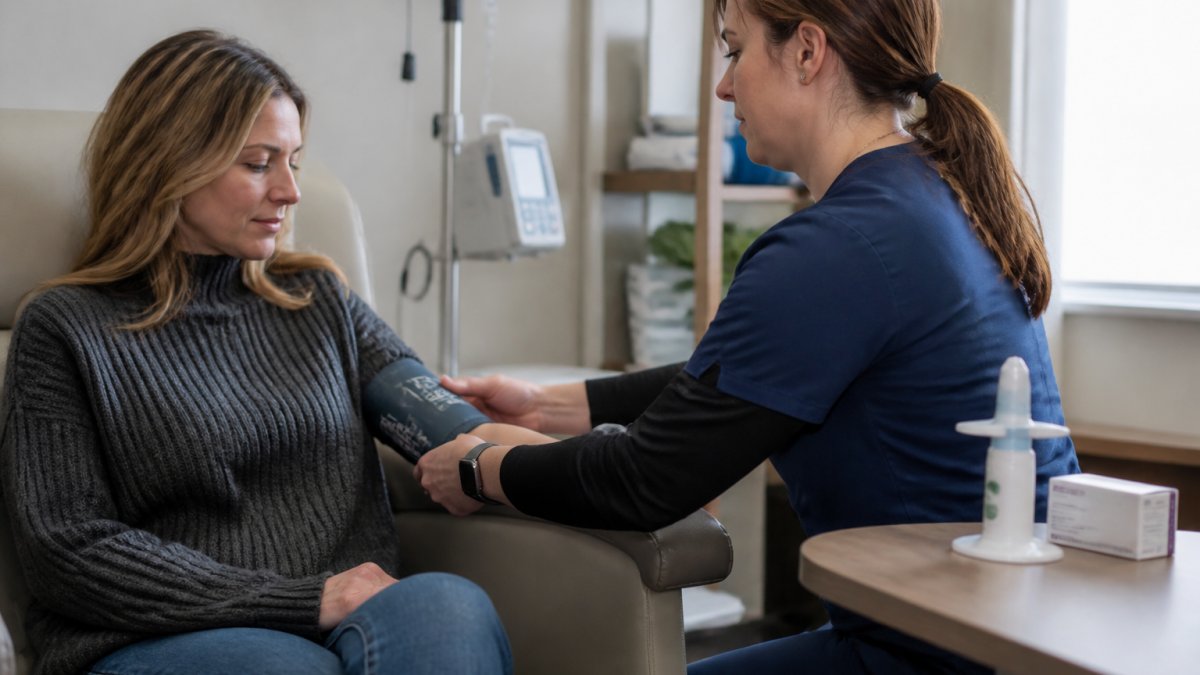
Esketamine, sold as Spravato, is an FDA-approved nasal spray for treatment-resistant depression and for depressive symptoms in adults with major depressive disorder who have suicidal thoughts or actions. It is a rapid-acting treatment, and that speed is the reason it sits at the top of this list.
How Esketamine Works
Esketamine is a derivative of ketamine that acts primarily on the NMDA glutamate receptor rather than on serotonin or norepinephrine. Glutamate is the brain's main excitatory neurotransmitter, and the NMDA pathway is involved in synaptic plasticity, the process by which connections between neurons strengthen or weaken. The leading hypothesis is that esketamine triggers a rapid burst of plasticity in mood-regulating circuits, which is why some patients report a change within 24 to 48 hours rather than the two to six weeks typical of oral antidepressants.
Who Qualifies and What to Expect
Eligibility generally requires a diagnosis of treatment-resistant depression and a history of failed antidepressant trials. The FDA-approved labeling specifies treatment-resistant depression in adults and depressive symptoms in adults with major depressive disorder who have suicidal thoughts or actions.
The practical schedule matters as much as the mechanism.
At Trust and Care Mental Health Inc, esketamine and Spravato are given in a monitored clinical environment, and treatment-only options are available for referring providers.
2. Transcranial Magnetic Stimulation for Depression
Transcranial magnetic stimulation, or TMS, is a noninvasive brain stimulation treatment that uses focused magnetic pulses to stimulate underactive areas of the brain involved in mood regulation. Repetitive TMS is the most common form, and it appeals to people who want a nonpharmacological option without anesthesia.
How TMS Works and Who It Helps
TMS is usually considered for adults with major depressive disorder who have not responded to antidepressants. Sessions are typically short, done in a clinic, and require no recovery time, but they run daily over several weeks. That schedule is the real hurdle: the treatment is well tolerated, yet it demands consistency.
A common mistake is treating TMS as a one-and-done fix. In practice, it works best as part of a combination treatment plan that includes therapy and ongoing medication review. Patients with certain implants or a history of seizures should discuss risks with their clinician first.
3. Electroconvulsive Therapy for Depression
Electroconvulsive therapy, or ECT, remains one of the most effective treatments for severe depression, particularly when symptoms are life-threatening, when psychosis is present, or when a patient cannot wait weeks for relief. Modern ECT is performed under general anesthesia with controlled electrical stimulation, a far cry from its depiction in older media.
Modern ECT: Safety and Effectiveness
The American Psychiatric Association's resource on ECT describes ECT as a safe and effective treatment for certain mental illnesses when administered properly. The main trade-off is memory side effects, which range from temporary confusion to longer-term gaps in recall. Patients weigh that risk against the severity of their depression.
ECT is not a last resort for hopeless cases. It is a legitimate medical procedure with decades of clinical evidence behind it, and for some patients it is the option that finally produces symptom relief.
4. Treatment-Resistant Depression Options: Adjunctive Medications
Adjunctive treatment means adding a second medication to an antidepressant that is already partially working. This is one of the most commonly used treatment-resistant depression options, and it deserves more attention than it usually gets.
Atypical Antipsychotics and Other Add-Ons
Adjunctive antipsychotics are among the best-studied add-on strategies for depression that responds only partially to standard therapy. Other add-ons include mood stabilizers and newer agents. Each carries its own side effect profile, so the choice comes down to matching the medication to your symptoms and health history.
5. Psychotherapy as an Advanced Treatment for Major Depressive Disorder
Psychotherapy is not just a first-line step; it functions as an advanced treatment when delivered in specialized forms. Cognitive behavioral therapy is the most studied, and it targets the thought patterns that feed depression. Acceptance and commitment therapy and other third-wave CBT approaches add strategies for tolerating difficult emotions rather than fighting them.
For chronic or recurrent depression, structured therapy is often what protects against relapse once medication or brain stimulation has lifted the acute symptoms. The evidence-based treatment combination of therapy plus medication tends to outperform either alone for moderate to severe depression.
How to Choose the Right Advanced Depression Treatment
Choosing comes down to three factors: severity and urgency, your treatment history, and what you can realistically commit to. Rapid relief matters if symptoms are dangerous. Schedule and tolerance matter if you need something sustainable over months. But the factor most guides skip is sequencing: advanced treatments are not a menu you pick from in any order. They are considered in a rough sequence based on how many adequate trials you have completed, how severe the episode is, and whether psychosis or suicidal intent is present.
A Practical Sequencing Framework
A common clinical pattern looks like this. After one failed antidepressant trial at adequate dose and duration, the usual next step is to optimize the current medication, switch to a different antidepressant, or add structured psychotherapy. After two failed trials, the treatment-resistant depression label applies, and the conversation shifts to esketamine, TMS, or adjunctive medication.
That framework is a starting point, not a rule. A board-certified psychiatrist adjusts it based on your full history, medical comorbidities, and prior response patterns.
Questions to Ask Before You Commit
Bring these to your consultation. They turn a general conversation into a specific plan:
- Which treatments am I eligible for based on my documented medication trials, and what documentation do you need from my prior prescriber?
- What is the expected time to response for each option, and how will we measure whether it is working?
- What are the most common side effects, and which ones would make us stop?
- How many sessions or doses does the full course require, and what does the schedule look like week by week?
- What is the plan if the first option does not work, and how long do we wait before switching?
- Is this treatment covered by my plan, what prior authorization is required, and what is my estimated out-of-pocket cost?
Cost, Coverage, and Access Realities
Cost is the factor patients ask about last and should ask about first. TMS and ECT are typically covered by commercial insurance and Medicare when medical necessity criteria are met, but prior authorization and session limits vary by plan. Esketamine is covered by many plans under the REMS framework but often requires documented treatment-resistant depression criteria.
Access barriers are real and worth naming. TMS requires daily visits for several weeks, which is difficult without transportation and schedule flexibility. ECT requires anesthesia and a recovery driver for each session. Esketamine requires a certified site and two-hour monitoring visits.
Red Flags That Should Change the Plan
Some situations should move you toward faster or more intensive options rather than watchful waiting: suicidal thoughts with a plan or intent, psychotic symptoms, catatonia, severe weight loss or dehydration, or a history of repeated relapse after apparently successful treatment.
Shared decision-making with a board-certified psychiatrist is the only reliable way to match a treatment to your situation. Outcome measures, such as symptom rating scales, help track whether a treatment is actually working, and they give you and your clinician a shared language for deciding when to continue, adjust, or switch.
Frequently Asked Questions
What are the most effective treatments for major depressive disorder when antidepressants fail?
When two or more antidepressants have not worked, clinicians consider advanced depression treatment options. These include esketamine nasal spray (Spravato), transcranial magnetic stimulation (TMS), electroconvulsive therapy (ECT), adjunctive atypical antipsychotics, and structured psychotherapy such as cognitive behavioral therapy. The best choice depends on symptom severity, medical history, side effect tolerance, and access to care. A psychiatrist can help match you with the right approach based on a thorough evaluation.
How does esketamine treatment for depression work, and is it safe?
Esketamine is an FDA-approved nasal spray used alongside an oral antidepressant for treatment-resistant depression. It targets glutamate pathways rather than serotonin, which may produce rapid symptom relief within hours to days. Because it can raise blood pressure and cause dissociation, it must be given in a certified clinical setting where staff monitor you for at least two hours after each dose. Your care team checks blood pressure and watches for side effects before you leave.
What is the difference between TMS and ECT for depression?
Transcranial magnetic stimulation (TMS) uses magnetic pulses to stimulate underactive brain regions without anesthesia, and patients remain awake. It is typically done in 20- to 40-minute sessions over several weeks and has few cognitive side effects. Electroconvulsive therapy (ECT) uses a brief electrical current under general anesthesia to produce a controlled seizure. ECT is often reserved for severe or life-threatening depression and can cause temporary memory issues, but it is highly effective for many people.
When is depression considered treatment-resistant, and what are the next steps?
Depression is generally considered treatment-resistant when two or more adequate trials of antidepressants from different classes fail to produce meaningful improvement. At that point, a psychiatrist may explore treatment-resistant depression options such as esketamine, TMS, ECT, or adding an adjunctive medication like an atypical antipsychotic. A thorough review of your medication history, side effects, and diagnosis is the first step. Ask your clinician about a structured plan and realistic timelines for response.



