comparison
Personalized Mental Health Treatment vs Enhanced Wellness
Table of Contents
- Personalized Mental Health Treatment Plans vs Enhanced Mental Wellness: Key Differences
- What Personalized Mental Health Treatment Means
- How Enhanced Mental Wellness Differs
- Treatment-Resistant Depression Treatment Options: A Comparison Table
- Depression Treatment Plan Examples: What Personalized Care Looks Like
- How to Talk to a Psychiatrist About Treatment-Resistant Depression
- Mental Wellness Strategies for Depression: What Works Alongside Clinical Care
- Safety, Access, and Coordinating Care
- Conclusion: Making an Informed Choice
- Frequently Asked Questions
Last Updated: October 15, 2026
Personalized Mental Health Treatment Plans vs Enhanced Mental Wellness: Key Differences
If you have tried two or more antidepressants without relief, you are not out of options. Personalized mental health treatment plans and enhanced mental wellness approaches are not competing philosophies; they are two layers of the same strategy, the first clinical and prescriptive, the second supportive and daily.
The distinction is not academic. According to the National Institute of Mental Health's overview of treatment-resistant depression, a meaningful share of adults with major depression do not respond fully to their first or second medication trial.
What Personalized Mental Health Treatment Means
Personalized mental health treatment is care built around one person's symptoms, history, biology, and preferences rather than a standard protocol.
That adaptation is the whole point. In practice, this means a care pathway that includes psychotherapy, medication management, and, for some patients, innovative treatments such as esketamine nasal spray.
Personalization also means shared decision-making. The patient is not handed a prescription and sent home; they help set treatment goals and weigh trade-offs.
How Enhanced Mental Wellness Differs
Enhanced mental wellness describes the daily practices and support systems that improve emotional well-being alongside clinical care. It is not a replacement for treatment.
Think of it as the foundation under the clinical work: sleep routines, movement, social connection, stress management, and structured self-monitoring. These habits support treatment engagement and quality of life but do not resolve treatment-resistant depression on their own.
The confusion arises when wellness content is marketed as a cure. For someone who has failed multiple medications, wellness strategies are an adjunct, not an alternative; skipping clinical care can delay effective treatment.
Treatment-Resistant Depression Treatment Options: A Comparison Table
Treatment-resistant depression is generally defined as depression that has not improved enough after at least two adequate trials of antidepressant medication, "adequate" meaning the right dose, taken consistently, for six weeks or more.
When a psychiatrist evaluates possible treatment resistance, they typically review:
- Which medications were tried, at what doses, and for how long
- Whether the patient took them as prescribed and tolerated them
- Whether the diagnosis is correct, or another condition (bipolar disorder, thyroid disease, sleep apnea, substance use) is driving symptoms
If two adequate trials have failed, the standard next step is a specialist evaluation rather than another round of the same. The table below compares the main approaches.
| Approach | What It Involves | Best For | Main Limitations | Typical Access and Cost Picture |
|---|---|---|---|---|
| Personalized medication management | Adjusting, combining, or switching medications based on response and tolerability | Patients who need refined drug therapy after one or more failed trials | Trial-and-error timeline; side effects; drug interactions | Covered by most insurance as psychiatric care; for current pricing, please check with Trust and Care Mental Health Inc directly. |
| Psychotherapy (including CBT) | Structured talk therapy targeting thoughts, behaviors, and relapse prevention | Building coping skills and preventing relapse | Requires time and consistent attendance; therapist availability varies widely | Often covered with a copay; for current pricing, please check with Trust and Care Mental Health Inc directly. |
| Combined treatment | Medication plus psychotherapy delivered together | Most patients with moderate to severe depression | Higher time and cost commitment | Usually the best-covered option because both components bill separately |
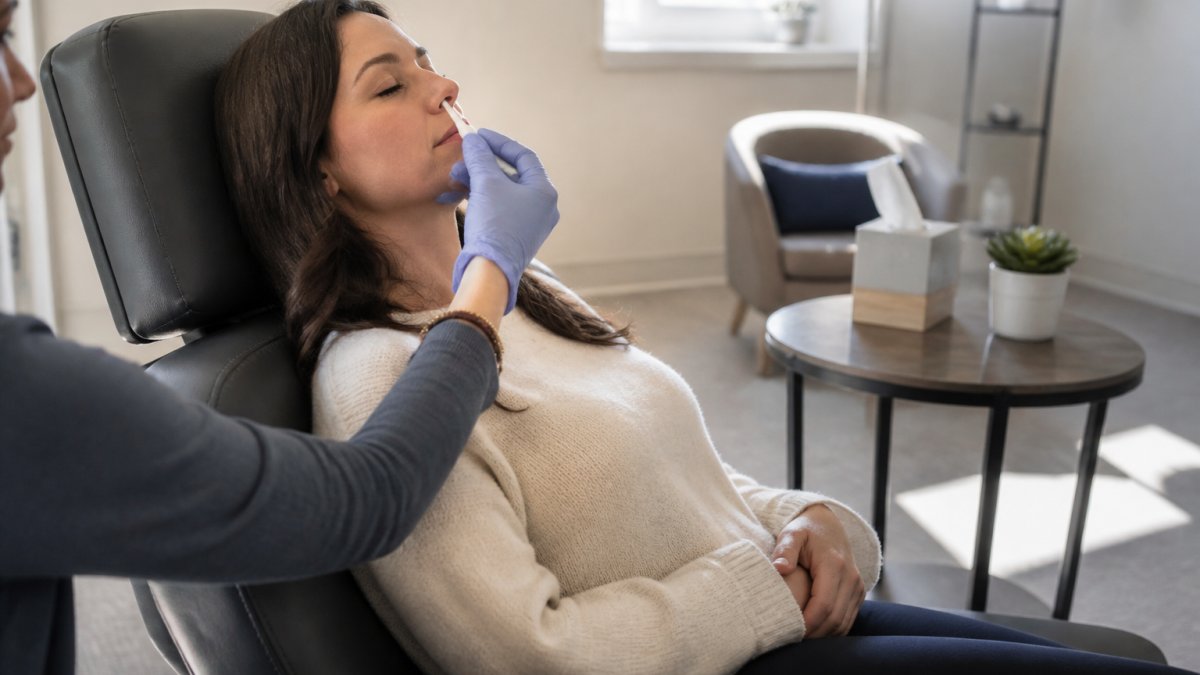
| Esketamine (Spravato) | FDA-approved nasal spray given in a certified, monitored setting | Adults with treatment-resistant depression | Requires observation for blood pressure and dissociation; not taken at home | Coverage varies by plan; prior authorization is common, and the drug plus monitoring is expensive without it |
| Neuromodulation (TMS, ECT) | Non-drug interventions that stimulate brain regions under clinical supervision | Selected patients who have not responded to medication | Time-intensive; eligibility criteria; cognitive effects with ECT | TMS is covered by many plans for qualifying patients; ECT is generally covered for severe or life-threatening depression |
| Enhanced mental wellness | Daily habits and support systems used alongside clinical care | Supporting any treatment plan; improving quality of life | Not a standalone treatment for resistant depression | Low direct cost; not a billable clinical treatment |
Pros and Cons of Each Option
Medication management offers targeted symptom relief but can take weeks and may bring side effects requiring adjustment. Psychotherapy builds durable skills and supports relapse prevention, though it demands consistent engagement and a good therapist fit. Combined treatment tends to outperform either alone for moderate to severe depression, at the cost of more appointments. Esketamine offers a faster option for difficult-to-treat cases but must be given in a monitored clinical setting because of blood pressure and dissociation effects.
What the Evidence Does and Does Not Show
Combined medication and psychotherapy has the strongest evidence base for moderate to severe depression. Esketamine is FDA-approved specifically for treatment-resistant depression, with meaningful but far from universal response rates, and requires ongoing monitoring. TMS and ECT have established roles for selected patients, with ECT generally reserved for more severe or urgent cases. Enhanced mental wellness practices, sleep regularity, movement, social connection, stress management, have supportive evidence for mood and quality of life, but not enough to claim they resolve treatment-resistant depression on their own.
How to Decide Between Them
The practical comparison usually comes down to four questions:
- How much clinician involvement do you want or need? Personalized plans and neuromodulation require regular clinical contact; wellness routines are largely self-directed.
- How much time can you commit? Weekly therapy plus medication management plus monitoring appointments adds up.
- What does your insurance cover? Prior authorization is common for esketamine and TMS, and psychotherapy coverage varies by plan and network.
- How urgent is your situation? If symptoms are severe or safety is a concern, the clinical pathway takes priority over any wellness layer.
A useful question to bring to a psychiatrist: "Given my history, what would you try next, and what would make you change course?"
Depression Treatment Plan Examples: What Personalized Care Looks Like
A depression treatment plan example might combine weekly cognitive behavioral therapy, a adjusted medication regimen, and a structured wellness routine, reviewed every few weeks against clear outcome measures.
The key feature is progress monitoring. Rather than waiting months to judge whether something works, a personalized plan sets checkpoints. If symptoms are not improving by an agreed point, the plan changes.
Case Example: Combining Psychotherapy and Medication
Consider a patient who has tried two antidepressants with partial response. A personalized plan might pair cognitive behavioral therapy with a medication adjustment, then reassess in four to six weeks. If response remains limited, the clinician and patient might discuss an FDA-approved option such as esketamine in a monitored setting. Throughout, wellness strategies support sleep, routine, and adherence. No single step is dramatic; the combination and the willingness to adjust are what move the needle.
How to Talk to a Psychiatrist About Treatment-Resistant Depression
Bring a written history: which medications you have tried, at what doses, for how long, and what happened. This single step makes the conversation far more productive.

Then ask directly about next steps. A psychiatrist experienced with treatment-resistant depression will walk through the care pathway, explain the reasoning behind each option, and set expectations for timelines and side effects.
Questions to Ask About Clinical Assessment and Treatment Goals
- What is your clinical assessment of my symptom severity and history?
- Which treatment goals should we set, and how will we measure progress?
- What are the options if this plan does not work?
Clear answers to these questions are a good sign you are in the right hands.
Mental Wellness Strategies for Depression: What Works Alongside Clinical Care
"Enhanced mental wellness" is not a clinical diagnosis, a drug, or a single program. It refers to a structured set of daily practices and support systems, sometimes delivered through an app, coaching program, or wellness framework, designed to improve emotional well-being alongside, not instead of, clinical care.
That distinction is the whole point of this comparison. A personalized treatment plan is clinical and prescriptive; enhanced mental wellness is supportive and daily. For treatment-resistant depression, the clinical plan is the priority, and wellness strategies make it easier to sustain.
What the Evidence Supports
The wellness practices with the strongest footing in care plans are practical and unglamorous:
- Keep a consistent sleep and wake schedule, since disrupted sleep is both a symptom and a trigger for depression
- Move your body most days, even briefly, regular physical activity has supportive evidence for mood
- Stay connected to one or two people regularly, because social isolation worsens depression outcomes
What the evidence does not support is the claim that these practices cure treatment-resistant depression. Wellness content is sometimes marketed as a substitute for clinical care, and that framing is inaccurate and risky. For someone who has failed multiple medication trials, wellness strategies are an adjunct, not an alternative; skipping clinical care can delay effective treatment.
How Wellness Fits Into a Personalized Plan
The most useful way to think about it is as a support layer that makes the clinical plan work better.
This is also where the two approaches overlap most productively. A clinician can review your wellness routine the way they review a medication: is it helping, is it sustainable, and should it change? That keeps wellness from becoming either an afterthought or an overpromise.
Questions to Ask Before Adding a Wellness Program
If you are considering a structured wellness program, app, or coaching service alongside treatment, ask:
- Is this meant to replace clinical care, or to support it?
- What evidence supports this specific program for depression?
- Will my clinician be able to see or use the data it collects?
A program that answers those questions clearly is more likely to be a genuine adjunct. One that promises to replace treatment for resistant depression is a red flag.
Safety, Access, and Coordinating Care
Safety comes first. Treatments such as esketamine require a monitored clinical setting because of blood pressure and dissociative effects, which is why administration is supervised rather than done at home.
Access and coordination matter too. Telehealth has widened access to psychiatric care, and coordination between a therapist, psychiatrist, and primary care provider keeps the plan consistent. When referring providers need treatment-only services, a clear handoff keeps the care pathway intact.
Conclusion: Making an Informed Choice
Personalized mental health treatment plans and enhanced mental wellness are not rivals; they are complementary. The clinical plan addresses the depression. The wellness layer supports the person living with it.
At Trust and Care Mental Health Inc, we combine traditional therapy with advanced medication management, including FDA-approved Spravato esketamine nasal spray, in a monitored clinical setting for safety and support.
Frequently Asked Questions
What is the difference between a personalized mental health treatment plan and a mental wellness plan?
A personalized mental health treatment plan is a clinical roadmap developed with a licensed professional. It includes diagnostic assessment, specific treatment goals, and evidence-based interventions such as psychotherapy, medication management, or procedures like Spravato. A mental wellness plan focuses on lifestyle habits and self-care strategies that support emotional health but do not replace clinical treatment. For treatment-resistant depression, a wellness plan works best alongside, not instead of, a personalized clinical plan.
What treatments are considered for treatment-resistant depression?
Treatment-resistant depression typically involves trying at least two different antidepressants without adequate relief. Options include adjusting or combining medications, adding psychotherapy such as cognitive behavioral therapy, and advanced interventions like esketamine nasal spray (Spravato), which is FDA-approved for treatment-resistant depression. Other possibilities include transcranial magnetic stimulation (TMS) and electroconvulsive therapy (ECT). A psychiatrist can help determine which option fits your symptoms, history, and preferences.
Can lifestyle changes help with treatment-resistant depression?
Lifestyle changes like regular exercise, consistent sleep, and stress-reduction techniques can support overall mental wellness, but they are not a standalone cure for treatment-resistant depression. They work best as part of a comprehensive plan that includes clinical care. Some people find that these strategies improve mood and energy, making it easier to engage in therapy or medication management. Always discuss lifestyle changes with your treatment team before making significant adjustments.
Can esketamine or Spravato be part of care for treatment-resistant depression?
Yes. Spravato (esketamine) is an FDA-approved nasal spray for adults with treatment-resistant depression, used alongside an oral antidepressant. It is administered in a certified clinical setting under supervision because it can cause dissociation and temporary blood pressure changes. A monitored environment ensures safety during and after each session. Your psychiatrist can assess whether Spravato is appropriate based on your medical history and previous treatment responses.