 ultimate-guide
The Long-Term Benefits of Esketamine for Depression
Last Updated: October 30, 2026
Quick Summary
The main long-term esketamine benefits are a longer time to relapse and sustained symptom control in treatment-resistant depression when esketamine is continued with an oral antidepressant after a patient responds to induction. The evidence supports durability over the medium term, roughly the first several months of maintenance, rather than indefinite benefit.
- Esketamine works through the glutamate system, not the serotonin pathway targeted by standard oral antidepressants.
- Induction is typically two sessions per week for the first four weeks, then dosing frequency is reduced.
- Response means roughly at least 50% improvement on a rating scale; remission means symptoms close to normal.
- Multi-year, placebo-controlled data are not available, so medium-term evidence is the honest limit.
- Stopping Spravato may increase the risk of depressive symptoms returning, so clinicians usually taper the schedule.
Table of Contents
- How Esketamine Works and Why Benefits Can Last
- The Evidence Behind Long-Term Esketamine Benefits
- Esketamine Maintenance Treatment: Keeping Symptoms in Remission
- How Long Can You Stay on Spravato?
- Long-Term Effects of Esketamine: Safety and Tolerability
- What Happens When You Stop Spravato
- Preparing for Your Esketamine Evaluation
- Frequently Asked Questions
How Esketamine Works and Why Benefits Can Last
Esketamine is a nasal spray formulation of ketamine, marketed as Spravato for treatment-resistant depression. It works through the glutamate system rather than the serotonin pathway targeted by standard oral antidepressants. That distinction matters: it means esketamine may produce a rapid antidepressant effect in some people who have not responded to conventional medications, and it has been studied as maintenance treatment.
The mechanism explains the durability. Standard antidepressants often take weeks to build up therapeutic levels. Esketamine triggers a faster cascade of neural changes.
For readers who want the mechanism compared directly with standard ketamine, our guide on the ketamine vs esketamine difference breaks down how the two compounds diverge in clinical use.
The Evidence Behind Long-Term Esketamine Benefits
The long-term case for esketamine rests on maintenance and extension studies in treatment-resistant depression, and the details matter more than the headline. In the pivotal maintenance trial, patients who met response criteria after an initial induction phase were randomized to continue esketamine plus an oral antidepressant or to switch to placebo plus an oral antidepressant. Continuing esketamine was associated with a longer time to relapse in the maintenance trial's follow-up window. That is the core evidence most guides summarize, but the design details are what tell you how far the finding travels.
What the studies actually measured. Relapse in these trials is typically defined as a return of depressive symptoms meeting a threshold on a rating scale, or a clinical decision that the patient needs a change in treatment. That is a meaningful outcome, but it is not the same as "staying well for years." Follow-up in the maintenance phase is measured in weeks to months, and extension studies that follow patients longer are open-label, meaning everyone knows they are receiving esketamine. Open-label extension data are useful for tracking safety and tolerability over time, but they are weaker evidence for efficacy than the randomized maintenance phase, because expectation and selection can inflate apparent benefit.
The limitation most guides skip. Attrition is the quiet problem in long-term psychiatric trials. Patients who do not tolerate a drug, or who relapse, tend to leave the study, which can make the remaining cohort look more stable than the full population starting treatment. When you read that a majority of patients maintained response, ask how many entered the extension and how many were still being counted at the end. The honest summary is that the evidence supports durability over the medium term, roughly the first several months of maintenance, and that multi-year, placebo-controlled data are not available for obvious ethical and practical reasons.
Esketamine evidence is not ketamine evidence. A frequent source of confusion is that search results blend esketamine trials with ketamine research. Esketamine is one form of ketamine, delivered as a nasal spray and studied in treatment-resistant depression populations. Racemic ketamine is used off-label, often intravenously, at different doses and on different schedules, and its long-term literature has its own design limits. A finding from an IV ketamine study does not automatically transfer to Spravato, and vice versa. Keeping the two evidence bases separate prevents overstating what is known about either.
For how those evidence limits translate into cost and scheduling decisions, our cost-benefit breakdown walks through the practical trade-offs.
Esketamine Maintenance Treatment: Keeping Symptoms in Remission
Maintenance is where the long-term benefits question actually gets answered, and it is more structured than most descriptions suggest. After a patient responds during induction, typically two sessions per week for the first four weeks, the schedule steps down. Dosing frequency is then reduced over time, with the exact interval set by the prescriber based on how the patient is doing. Each session takes place under clinical supervision, with blood pressure monitoring before and after dosing.
Response and remission are not the same milestone. Response generally means a meaningful reduction in depressive symptoms, often framed as at least a 50% improvement on a rating scale. Remission means symptoms have fallen into a range considered close to normal, sustained over time. A patient can respond without reaching remission, and a patient can reach remission and still relapse. Maintenance is the phase that defends remission, and the reason clinicians do not stop at the first good week is that the relapse data show the risk is concentrated in the months after acute treatment ends.
What long-term benefit looks like beyond a symptom score. Rating scales are how trials measure benefit, but patients usually care about something more concrete: getting back to work, re-engaging with family, sleeping through the night, and not cycling in and out of crisis. The evidence here is thinner and mostly comes from secondary outcomes and patient-reported measures in maintenance studies rather than from dedicated functional-outcome trials. A reasonable reading is that patients who sustain remission often report improved functioning and quality of life, but the field has not established how much of that is esketamine specifically versus the combination of continued treatment, monitoring, and the structure of care. That uncertainty is worth naming rather than papering over.
Maintenance intervals are a negotiation, not a fixed prescription. Some patients hold steady on every-two-week dosing; others need to stay weekly longer, and some step back to weekly after a stressful period or early warning signs. The schedule is reviewed at each visit against symptom scores, side effects, and blood pressure trends. This is also where treatment burden enters the benefit-risk conversation: every session means travel, a monitored recovery period, and time away from work or caregiving. A maintenance plan that ignores that burden tends to fail on adherence rather than on pharmacology.
Subgroups and uncertainty. The maintenance evidence is strongest for adults with treatment-resistant depression who responded to induction. Older adults, people with significant cardiovascular disease, and those with active substance use concerns require closer individual assessment, and the long-term data for those groups are more limited. A balanced decision weighs the sustained-benefit signal against monitoring requirements, tolerability, and the honest gaps in multi-year evidence, with a clinician who knows your history, not a generic protocol.
How Long Can You Stay on Spravato?
Duration is decided case by case between you and your prescribing clinician, based on how well you are tolerating the treatment and whether your depressive symptoms remain controlled.
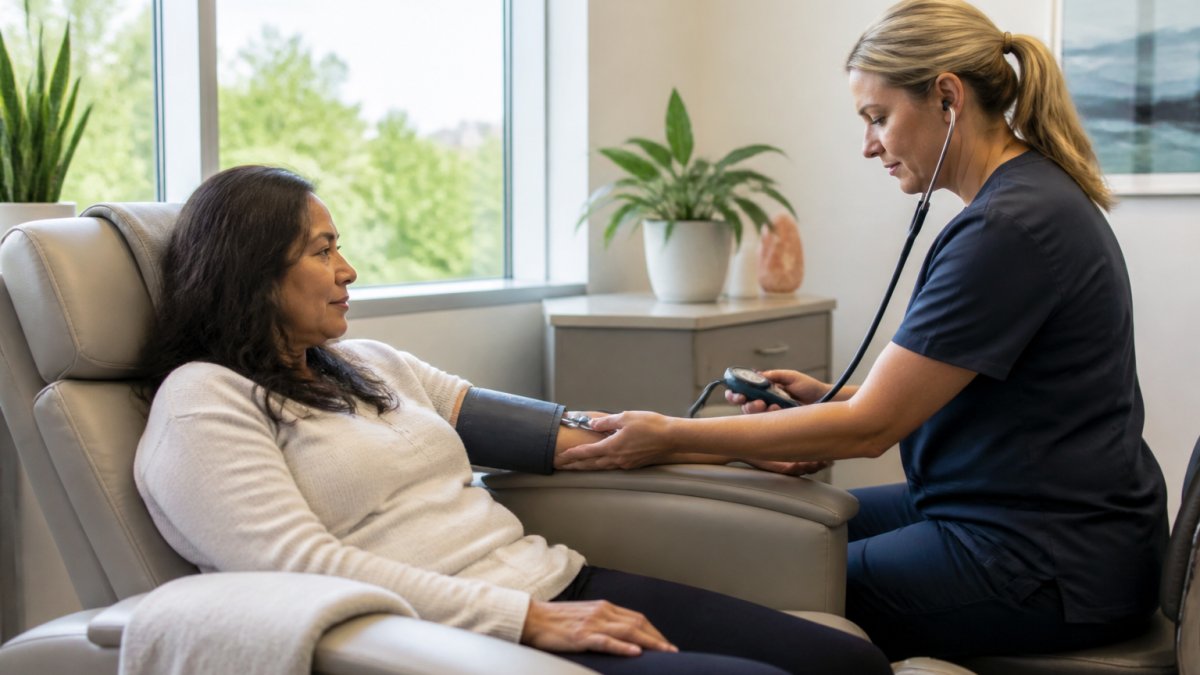
The decision to continue is reviewed regularly, not set once. At Trust and Care Mental Health Inc, sessions take place in a monitored clinical setting.
Long-Term Effects of Esketamine: Safety and Tolerability
Esketamine is administered under clinical monitoring. The most discussed short-term effects, dissociation and temporary blood pressure rises, are the reason Spravato must be given under clinical monitoring. Over repeated treatment, tolerability is tracked session by session.
| Concern | What Monitoring Involves | Why It Matters |
|---|---|---|
| Blood pressure | Checked before and after dosing | Catches temporary spikes early |
| Dissociation | Observed during the session | Confirms you are safe to leave |
| Drowsiness | Supervised recovery time | Prevents impaired driving |
| Urinary symptoms | Reviewed at follow-up | Flags issues needing attention |
For a closer look at how side effects are tracked over time, see our Spravato monitoring guide, and for practical coping strategies during ongoing treatment, read managing side effects during esketamine therapy.
What Happens When You Stop Spravato
Stopping Spravato may increase the risk of depressive symptoms returning. The clinical concern after stopping is that depressive symptoms may return, which is why clinicians usually taper the schedule rather than stop abruptly. Some patients transition back to oral antidepressants alone; others resume esketamine if symptoms recur.
Ask your clinician upfront how discontinuation will be handled, and what warning signs would prompt a return to treatment.
Preparing for Your Esketamine Evaluation
An evaluation confirms whether esketamine is appropriate for your situation. An evaluation typically includes a review of your medication history and current symptoms, along with any conditions relevant to treatment safety. Bring a list of everything you take.
If you are ready to begin, our five ways to prepare for your first session covers what to arrange beforehand. A risk-benefit assessment with a qualified clinician is the right next step, not a decision made alone.
Frequently Asked Questions
How long do the effects of esketamine last?
The rapid antidepressant effect of a single esketamine dose can appear within hours to a day, but that early response is short-lived on its own. Some studies have examined continued dosing on a schedule as a way to maintain symptom improvement. Your care team will discuss the schedule with you based on how you respond.
Can esketamine help prevent depression from returning?
Maintenance studies have examined whether continued esketamine alongside an oral antidepressant can reduce relapse in treatment-resistant depression. Results vary between individuals, and relapse prevention is not guaranteed. Ongoing monitoring and an honest conversation with your psychiatrist about warning signs are part of any maintenance plan.
What happens when you stop taking esketamine?
Depressive symptoms can return if the underlying condition is not otherwise controlled. Plan any change to your treatment schedule with the prescriber who has been monitoring you. Never stop on your own; plan the transition with the prescriber who has been monitoring you.
How long can you stay on Spravato?
Duration of treatment is decided with your prescribing clinician based on the risk-benefit balance for your situation, and it is reviewed over time.
Who should not take esketamine?
Esketamine is not appropriate for everyone. Whether it fits your situation depends on a full medical review with a qualified clinician.
Treatment-resistant depression is exhausting, and the decision to try something new deserves a team that monitors you closely. Trust and Care Mental Health Inc offers FDA-approved Spravato esketamine nasal spray in a monitored clinical setting, with treatment-only options for referring providers and personalized plans for adults, older adults, and families. Make your appointment today and take the next step toward steadier symptom control.



